


Direktang sagot
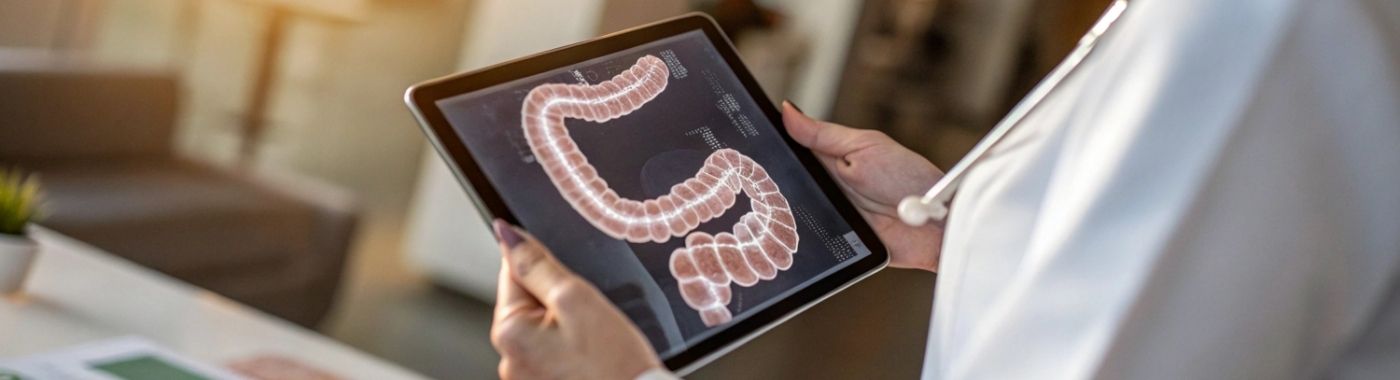
A colonoscopy is an endoscopic examination in which a thin flexible camera tube is passed through the rectum to inspect the lining of the entire large intestine. Colonoscopy allows biopsy and removal of polyps in the same sitting. Colonoscopy is used for colorectal cancer screening, for bleeding or bowel-habit change, and for monitoring inflammatory bowel disease.
Key takeaways
- Colonoscopy both examines and treats, polyps can be removed and tissue sampled during the same procedure.
- Colonoscopy quality depends heavily on bowel preparation; poor preparation can hide flat lesions and may mean the test has to be repeated.
- A normal colonoscopy does not rule out disease outside the large bowel, and does not detect every lesion.
- Colonoscopy reaches parts of the bowel that sigmoidoscopy and stool tests cannot, but it is not automatically the right first test for every symptom.
- Results vary depending on individual clinical circumstances and must be interpreted by the doctor who requested the procedure.
Sa isang sulyap
| tampok | detalye |
|---|---|
| What is examined | Rectum, sigmoid, descending, transverse and ascending colon, caecum; often the last few centimetres of the ileum |
| Procedure time | Commonly around 20-45 minutes; longer if polyps are removed |
| Total time in hospital | Usually several hours including check-in, sedation and recovery |
| Pagbubuntis | Usually conscious sedation or short general anaesthesia; some units offer unsedated procedures |
| Paghahanda | Low-residue diet, clear fluids, prescribed bowel-cleansing solution |
| Escort needed | Yes, if sedation is used, you cannot drive or ride home alone |
| Can treat as well as diagnose | Yes, polypectomy, biopsy, bleeding control, dilatation in selected cases |
| Report available | Endoscopy findings usually the same day; biopsy or polyp histopathology takes longer |
Kilala rin bilang
- Lower GI endoscopy
- Large bowel endoscopy / large intestine camera test
- Colon camera test, "colon scopy"
- Bade aant ki jaanch (large intestine examination)
- Related but distinct: sigmoidoscopy, proctoscopy, upper GI endoscopy (gastroscopy)
What a colonoscopy is
A colonoscope is a flexible tube about the thickness of a finger, carrying a light, a camera and channels through which air or carbon dioxide, water and instruments can pass. The endoscopist advances the colonoscope from the rectum around to the caecum, then examines the lining carefully while withdrawing. Images appear on a monitor and are recorded.
Because instruments can be passed through the scope, colonoscopy is both diagnostic and therapeutic. Polyps can be snared or resected, small bleeding points can be clipped or cauterised, biopsies can be taken from inflamed or suspicious areas, and narrowed segments can sometimes be dilated or stented.
Why a colonoscopy is done
- Dumudugo: visible rectal bleeding, blood mixed with stool, or iron-deficiency anaemia without an obvious cause.
- Change in bowel habit: persistent new diarrhoea, constipation or narrowing of stool calibre.
- Polyp detection and removal: removing adenomatous polyps reduces the risk of colorectal cancer developing, though it does not eliminate it.
- Colorectal cancer screening and surveillance: in average-risk and higher-risk groups, and after previous polyps or cancer.
- Mga nagpapasiklab na sakit sa bituka: diagnosing and mapping ulcerative colitis and Crohn's disease, assessing healing, and dysplasia surveillance in long-standing colitis.
- Chronic unexplained abdominal pain or weight loss where bowel pathology is suspected.
- Follow-up of abnormal imaging or a positive stool test such as a positive faecal occult blood or faecal immunochemical test.
- Suspected chronic infection: in India, intestinal tuberculosis and amoebic colitis are important considerations, and biopsy is often needed to distinguish intestinal TB from Crohn's disease.
Who should consider a colonoscopy
- Adults with rectal bleeding, unexplained iron-deficiency anaemia, or a persistent unexplained change in bowel habit, the specific test and its timing depend on age and symptoms.
- People eligible for colorectal cancer screening. International guidance commonly begins average-risk screening in the mid-40s; India has no universal population screening programme, so screening is usually individualised after a discussion of family history and risk.
- People with a first-degree relative who had colorectal cancer or advanced polyps, who generally need earlier and more frequent examination.
- People with known or suspected hereditary syndromes such as Lynch syndrome or familial adenomatous polyposis, who follow dedicated surveillance schedules.
- People with long-standing ulcerative colitis or Crohn's colitis needing dysplasia surveillance.
- People with a positive stool-based screening test.
Colonoscopy is not the right test for everyone. Frail people, those with severe cardiorespiratory disease, or those in whom a full examination is unlikely to change management may be better served by a limited examination or CT colonography. Your gastroenterologist will decide with you.
What a colonoscopy cannot detect or exclude
- It does not examine the small intestine beyond the last few centimetres of the ileum. Small bowel bleeding or Crohn's disease higher up can be missed; capsule endoscopy, enteroscopy or MR enterography may be needed.
- It does not examine the stomach or oesophagus. Anaemia or bleeding may require an upper GI endoscopy as well.
- It looks at the lining, not the layers beyond it. Depth of tumour invasion, lymph nodes and spread need CT, MRI or endoscopic ultrasound.
- Lesions can be missed. Flat and right-sided lesions, lesions behind folds, and lesions hidden by residual stool are the usual reasons. Interval cancers can occur after a normal colonoscopy, so no colonoscopy report should be read as a guarantee.
- An incomplete colonoscopy examines less than the whole colon. If the caecum was not reached because of a tight bend, adhesions, a narrowing or discomfort, the unexamined segment has simply not been assessed.
- It cannot diagnose functional bowel disorders directly. Irritable bowel syndrome is a clinical diagnosis; colonoscopy mainly helps exclude alternative structural or inflammatory causes.
- "No abnormality seen" means nothing abnormal was visualised: it is not the same as disease being excluded. If your symptoms continue, bleeding recurs, or new symptoms appear despite a normal colonoscopy, go back to your doctor rather than assuming the problem has been settled.
Mga kaugnay ngunit magkaibang pagsusuri
| pagsusuri | Ang sagot nito | Mga pangunahing pagkakaiba |
|---|---|---|
| Colonoscopy | What does the lining of the whole large bowel look like, and can lesions be removed or sampled now? | Full bowel preparation, usually sedation, allows biopsy and polypectomy |
| Flexible na sigmoidoscopy | Is there disease in the rectum and left colon? | Limited preparation, often no sedation, quicker; does not assess the right colon |
| Proctoscopy / matibay na sigmoidoscopy | Are there haemorrhoids, fissures or rectal lesions? | Office procedure, very limited reach |
| CT colonography | Are there structural lesions in a bowel that cannot be intubated? | Still needs bowel preparation, uses radiation, cannot biopsy or remove polyps; abnormal findings usually lead to colonoscopy |
| Stool tests (FIT / faecal occult blood) | Is there occult blood suggesting a need for further investigation? | Non-invasive, no preparation, repeated at intervals; a negative test does not exclude cancer or polyps |
| Capsule endoscopy | Is there small bowel disease? | Swallowed camera; no tissue sampling; not a colonoscopy substitute |
| Endoscopy sa itaas na GI | Is there disease in the oesophagus, stomach or duodenum? | Different scope, different route; often combined with colonoscopy for anaemia |
These are not ranked from worst to best. They answer different questions. Which one comes first depends on the clinical problem, visible rectal bleeding in an older adult, an asymptomatic person due for screening, and suspected proctitis are three different situations with three different sensible starting points.
How to prepare for a colonoscopy
Preparation regimens differ between hospitals and endoscopy units, and depend on the bowel-cleansing product used, the time of your appointment and your medical history. Written instructions from the unit performing your procedure take precedence over anything general you read here.
- Diyeta: most units advise a low-residue diet (avoiding seeds, nuts, skins, whole grains, raw vegetables) for a few days, then clear fluids for a defined period before the procedure.
- Bowel-cleansing solution: taken as a split dose in most protocols, with part on the evening before and part on the morning of the procedure. Follow the exact volume and timing your unit gives you.
- Mga likido: clear fluids are usually allowed until a specified time; units differ in their final cut-off.
- Gamot: tell the team about blood thinners, antiplatelet drugs, insulin and other diabetes medicines, iron tablets, and any AYUSH, herbal or gym supplements. Do not start, stop or alter any prescribed medicine yourself, ask the prescriber or the endoscopy team what to do.
- Escort and consent: if sedation is planned, arrange for a responsible adult to accompany you home. Plan not to drive, ride a two-wheeler, operate machinery or sign legal documents for the rest of the day.
pagbubuntis
Colonoscopy in pregnancy is performed only when clearly necessary, in consultation with the obstetric team, with attention to positioning, sedation choice and timing. Bowel-preparation products and fluid shifts need specific assessment.
Mga bata at mga kabataan
Paediatric colonoscopy uses weight-based preparation and is generally done under anaesthesia in a paediatric setting. Adult preparation volumes must never be applied to a child.
Diyabetis na nasa therapy na nagpapababa ng glucose
Fasting plus bowel preparation carries a real risk of hypoglycaemia. Insulin and other glucose-lowering medicine schedules usually need adjustment by the prescribing doctor, and blood glucose should be monitored during preparation. Ask for explicit written instructions.
Chronic kidney disease, heart failure and fluid restriction
Large-volume bowel preparations cause fluid and electrolyte shifts. People with advanced CKD, heart failure, cirrhosis with ascites or a prescribed fluid restriction need a preparation chosen and supervised by their treating doctor. Phosphate-containing preparations are avoided in these groups in many units.
Mas matatanda
Preparation is more likely to cause dehydration, giddiness and falls. Extra supervision at home during preparation is sensible, and sedation is usually titrated more cautiously.
Blood thinners and bleeding disorders
Anticoagulants and antiplatelet drugs affect the bleeding risk of polyp removal, and stopping them carries its own risks. The decision belongs to the prescribing cardiologist or physician together with the endoscopist.
Implants, pacemakers and other devices
Tell the team about pacemakers, implantable defibrillators and any implanted device, as electrocautery settings may need adjustment.
What happens during a colonoscopy
- Check-in: consent, allergy and medication review, a cannula for sedation, and monitoring of pulse, blood pressure and oxygen saturation.
- positioning: you lie on your left side with knees drawn up, in a gown.
- Pagpapatahimik: given intravenously in most cases. Some people have a short general anaesthetic; some units offer the procedure without sedation.
- Examination: the colonoscope is advanced gently, with gas used to open the bowel. Carbon dioxide, where available, is absorbed faster and tends to cause less bloating than air. Position changes and abdominal pressure are often used to negotiate bends.
- Therapy: polyps are removed with a snare or forceps; biopsies are taken where needed; clips or cautery may be used to stop bleeding. Specimens go to histopathology.
- Pagbawi: monitored until sedation wears off, then fluids and light food if allowed. Bloating and passing gas are common for a few hours.
Gaano katagal ang proseso
- Paghahanda: spans the day before and the morning of the procedure, depending on the regimen.
- Pamamaraan: commonly around 20-45 minutes; longer with multiple or difficult polyps.
- Recovery after sedation: typically one to a few hours in the unit.
- Buong araw: plan to be away from work for the day of the procedure, and for part of the preceding day.
- Histopathology: takes additional days; the endoscopy findings and the biopsy report are two separate documents.
Understanding your colonoscopy report
An endoscopy report usually records how far the scope reached, how good the bowel preparation was, what was seen, what was done, and what follow-up is advised. These details matter as much as the headline finding.
- Lawak: "caecal intubation achieved" means the whole colon was reached. If not, the report should say how far the examination went.
- Preparation quality: often scored descriptively or with a scale. Poor preparation lowers confidence in the result and may prompt an earlier repeat.
- Normal mucosa: no visible abnormality in the segments examined.
- Mga polyp: described by number, size, site and appearance. Whether a polyp matters depends on its histology, hyperplastic, adenomatous, serrated, which only the biopsy report can tell you.
- Inflammation, ulcers or erosions: a pattern, not a diagnosis. Differentiating ulcerative colitis, Crohn's disease, infective colitis, intestinal tuberculosis, ischaemic colitis and drug-related injury needs biopsy and clinical correlation.
- Diverticulosis: pouches in the colon wall, common with age and often incidental.
- Almoranas: frequently reported and often not the cause of significant symptoms; bleeding still needs the rest of the bowel accounted for.
- Mass or stricture: a suspicious lesion is described and biopsied. A visual impression is not a cancer diagnosis until histopathology confirms it.
Colonoscopy descriptions of severity are partly subjective and vary between endoscopists. Do not grade your own prognosis from adjectives in the report. The doctor who requested the procedure interprets it alongside your symptoms, blood tests, imaging and histopathology.
When colonoscopy results can be misleading
Findings that may be falsely reassuring (missed or under-called disease)
- Inadequate bowel preparation obscuring flat or small lesions.
- Incomplete examination where the right colon was never reached.
- Rapid withdrawal, so the lining is inspected less carefully.
- Flat, serrated or right-sided lesions, which are inherently harder to see.
- Disease outside the colon, small bowel, stomach, pancreas, gynaecological or urological, that a colonoscopy was never going to show.
- Patchy Crohn's disease or early inflammation that looks near-normal on the surface but shows changes only on biopsy.
Findings that may overstate disease
- Preparation-related redness, or trauma from the scope, mimicking inflammation.
- Recent NSAID use causing erosions or ulcers unrelated to inflammatory bowel disease.
- Prominent haemorrhoids or vascular markings over-interpreted as a bleeding source.
- Lymphoid hyperplasia in children and young adults, a normal variant.
- Benign strictures from healed inflammation, ischaemia or previous surgery mistaken for tumour until biopsy clarifies.
Mga panganib at kaligtasan
Colonoscopy is widely performed and serious complications are uncommon, but they are real, and the risk is not the same for every version of the procedure. Risk depends on age, comorbidity, sedation, and whether therapy was performed.
Diagnostic colonoscopy without therapy
Bloating, cramping and transient discomfort are common. Perforation and significant bleeding are uncommon in purely diagnostic examinations.
Colonoscopy with polypectomy or resection
Removing polyps adds a bleeding risk, which can occur days later, and a higher perforation risk than diagnostic examination alone. Larger lesions, piecemeal resection and endoscopic mucosal or submucosal dissection carry greater risk and may involve a short hospital stay.
Sedation and anaesthesia
Risks include low blood pressure, low oxygen levels, breathing depression and, rarely, aspiration or cardiac events. People with sleep apnoea, significant heart or lung disease, or obesity need pre-procedure anaesthetic assessment.
Paghahanda ng bituka
Dehydration, nausea, vomiting and electrolyte disturbance can occur, more so in older adults and in those with kidney, heart or liver disease. Seizures from severe electrolyte disturbance are rare but reported.
iba
Infection is rare with properly reprocessed equipment. Post-polypectomy syndrome, splenic injury and missed lesions are recognised but infrequent. Results and complication rates vary depending on individual clinical circumstances.
Red flags after a colonoscopy
Emergency: humingi ng tulong medikal ngayon
- Severe or steadily worsening abdominal pain, or a rigid, very tender abdomen.
- Heavy rectal bleeding, passing large clots, or bleeding that does not stop.
- Fainting, severe giddiness, cold clammy skin or a racing pulse.
- Hirap sa paghinga o pananakit ng dibdib.
- Repeated vomiting with abdominal distension and inability to pass gas.
- Fever with severe abdominal pain.
Same day: contact the endoscopy unit or your doctor today
- Small amounts of fresh bleeding continuing beyond the first day, or recurring after polyp removal.
- Fever without severe pain.
- Persistent cramping that is not settling after several hours.
- Inability to keep fluids down.
- Confusion or marked weakness after preparation, especially in older adults or people with diabetes, CKD or heart failure.
Regular na appointment
- Discussing biopsy or polyp histopathology results and follow-up interval.
- Mild bloating or a small streak of blood that settles within a day.
- Symptoms that persist or return despite a normal colonoscopy, these still need review.
- Planning repeat surveillance, or reviewing a report that says preparation was poor or the examination was incomplete.
Mga espesyal na sitwasyon
pagbubuntis
Colonoscopy is deferred unless the information is needed for immediate management. Decisions are shared between the gastroenterologist, obstetrician and anaesthetist, with attention to sedation agents and maternal positioning.
Mga bata
Indications differ from adults and include inflammatory bowel disease, polyposis syndromes and chronic bleeding. Paediatric-calibre scopes, anaesthesia and weight-based preparation are standard.
Mas matatanda
Benefit depends on life expectancy and comorbidity as much as on age. Preparation tolerance, dehydration, falls and sedation risk all weigh in the decision, and a limited examination or CT colonography is sometimes more appropriate.
Diyabetis na nasa therapy na nagpapababa ng glucose
Hypoglycaemia during preparation and fasting is the main hazard. Written medication instructions from the prescriber and home glucose monitoring during preparation are important. Early-morning appointment slots are often preferred.
Talamak na sakit sa bato at pagpalya ng puso
Preparation choice and volume must be individualised. Certain preparations are avoided, and supervised or modified regimens are used in advanced disease.
Nagpapaalab na sakit sa bituka
Colonoscopy is used for diagnosis, assessing mucosal healing and dysplasia surveillance in long-standing colitis, often with dye-spray or high-definition techniques and multiple biopsies.
Previous abdominal or pelvic surgery, or prior radiotherapy
Adhesions and altered anatomy can make a complete examination difficult and may increase the chance of an incomplete procedure.
Colonoscopy in the Indian context
- Infections matter more here. Intestinal tuberculosis, amoebiasis and other infective colitides can closely mimic Crohn's disease. Biopsies for histopathology, acid-fast staining and molecular testing are often taken specifically to make this distinction, and repeat colonoscopy after a treatment trial is sometimes needed.
- Anaemia is common and has many causes. Iron-deficiency anaemia in India often has nutritional or parasitic contributors, and thalassaemia trait is prevalent. That does not remove the need to look for a bowel source of bleeding when clinical features suggest one.
- No national screening programme. Colorectal cancer screening in India is largely opportunistic and doctor-led rather than population-based, so the decision to screen is individual and depends on family history and risk factors.
- Haemorrhoids are over-blamed. Rectal bleeding is frequently attributed to piles without further evaluation. Haemorrhoids are common, but their presence does not account for anaemia, weight loss, altered bowel habit or bleeding in an older adult.
- Supplements and self-medication. Herbal, AYUSH and gym supplements, along with NSAIDs and laxative overuse, can cause bowel or liver injury. Bring an accurate list of everything you take.
- Pagkalihim ng datos. Endoscopy images, reports and any online appointment or enquiry forms involve personal health data, which is handled under the Digital Personal Data Protection Act, 2023.
- Professional conduct. Consent, disclosure of risk and communication of results are governed by National Medical Commission professional conduct standards.
Gastos at seguro sa India
Costs for colonoscopy in India vary very widely between cities, between government and private facilities, and between a simple diagnostic examination and one involving multiple polypectomies. Because of that variation, no single figure is meaningful; ask the performing unit for a written estimate before booking.
Factors that change the cost:
- Diagnostic colonoscopy versus polypectomy, mucosal resection, dilatation or stenting.
- Sedation versus general anaesthesia, and whether an anaesthetist is present.
- Number of biopsy specimens and histopathology charges, which are billed separately.
- Bowel-preparation medication, consumables such as snares, clips and injection needles.
- Day-care versus inpatient admission, and room category.
- City, hospital tier and whether the facility is government, trust or corporate.
- Pre-procedure tests such as blood counts, coagulation profile, ECG or anaesthetic review.
Seguro: colonoscopy done as day-care treatment for a diagnosed or suspected condition is covered by many Indian health insurance policies, but purely screening or preventive procedures in an asymptomatic person are often excluded. Waiting periods, pre-existing disease clauses, day-care listings and sub-limits all apply. Government schemes such as Ayushman Bharat PM-JAY cover eligible beneficiaries at empanelled hospitals under defined packages. Confirm coverage and pre-authorisation with your insurer or the hospital's insurance desk before the procedure.
Mga alamat at katotohanan
| Katha-katha | Katotohanan |
|---|---|
| A normal colonoscopy means my bowel is fine for ten years, whatever happens | Recommended intervals assume a complete examination with good preparation and no new symptoms. New bleeding, weight loss or change in bowel habit needs fresh assessment regardless of when the last colonoscopy was. |
| Colonoscopy is unbearably painful | Most people have sedation and recall little discomfort. Bloating and cramping afterwards are common and usually short-lived. |
| Rectal bleeding in a young person is always piles | Haemorrhoids are the commonest cause but not the only one. Persistent bleeding, anaemia or altered bowel habit needs evaluation. |
| All polyps are cancer | Most polyps are not cancer. The histopathology report determines whether a polyp had any premalignant potential and what follow-up is needed. |
| A stool test can replace colonoscopy | Stool tests are useful screening tools but cannot remove polyps or take biopsies, and a negative stool test does not exclude significant disease. |
| Bowel preparation is optional if I eat lightly | Without proper cleansing, lesions are hidden and the examination may need repeating. Eating lightly is not a substitute for prescribed preparation. |
| Colonoscopy spreads cancer | There is no evidence that colonoscopy spreads colorectal cancer. Delaying evaluation of worrying symptoms is the greater risk. |
Mga madalas itanong
Masakit ba ang colonoscopy?
Most colonoscopies are done with intravenous sedation, and people usually remember little of the procedure. Some units offer unsedated colonoscopy, where cramping during loop formation can be uncomfortable but is generally brief. Bloating and wind afterwards are common. Tell the team if you have had a difficult examination before.
Ano ang pagkakaiba ng colonoscopy at sigmoidoscopy?
Flexible sigmoidoscopy examines only the rectum and left colon, needs lighter preparation and often no sedation. Colonoscopy examines the entire large bowel including the right colon, which sigmoidoscopy cannot reach. Sigmoidoscopy is reasonable for suspected rectal or left-sided disease; it does not replace a full colonoscopy when the whole colon needs assessment.
Gaano kabilis ko makukuha ang aking mga resulta?
The endoscopist usually explains the visual findings on the same day, once sedation has worn off, and gives a written endoscopy report. Histopathology on biopsies or removed polyps takes longer and comes as a separate report. Final advice on follow-up intervals often waits for that histopathology result.
Can I eat normally after a colonoscopy?
Most units allow fluids and then light food once sedation has worn off and you are comfortable. If a large polyp was removed, a stricture dilated, or a complication is suspected, the team may advise a restricted diet for a period. Follow the specific discharge instructions you are given.
What if my colonoscopy could not be completed?
An incomplete colonoscopy means part of the colon was not examined, usually because of looping, adhesions, a narrowing or poor preparation. That segment has not been assessed. Options include a repeat colonoscopy, sometimes with a different technique or anaesthesia, or CT colonography to image the unexamined bowel.
How often should a colonoscopy be repeated?
Intervals depend on why the colonoscopy was done, the quality of the examination, family history, and the number, size and histology of any polyps removed. People with inflammatory bowel disease or hereditary syndromes follow separate surveillance schedules. Your gastroenterologist will set the interval after seeing the histopathology report.
Do I need to stop my blood thinner before a colonoscopy?
Sometimes, but that decision is not yours to make alone. Stopping anticoagulant or antiplatelet medicine carries its own risk of clotting events, while continuing it increases bleeding risk if polyps are removed. Ask the prescribing doctor and the endoscopy team well before your appointment, and follow their written plan.
Can I go back to work the same day?
If you had sedation, plan to rest for the remainder of the day. Judgment and reflexes can remain affected for several hours, so avoid driving, riding a two-wheeler, operating machinery or signing important documents. Most people return to normal activity the next day, unless a therapeutic procedure requires longer recovery.
Is CT colonography a good alternative?
CT colonography can show structural lesions and is useful when colonoscopy is incomplete, high-risk or declined. It still needs bowel preparation, uses radiation, and cannot take biopsies or remove polyps. Significant findings on CT colonography usually lead to a colonoscopy anyway, so it is an alternative in specific situations rather than a general substitute.
Pinagmumulan ng
- World Health Organization / International Agency for Research on Cancer, GLOBOCAN colorectal cancer statistics and India factsheets.
- Indian Council of Medical Research, National Cancer Registry Programme reports.
- Indian Society of Gastroenterology, position and consensus statements on colonoscopy practice and on differentiating intestinal tuberculosis from Crohn's disease.
- American Society for Gastrointestinal Endoscopy, guidelines on bowel preparation, sedation, antithrombotic management and post-polypectomy surveillance.
- British Society of Gastroenterology / European Society of Gastrointestinal Endoscopy, colonoscopy quality standards and surveillance guidance.
- Digital Personal Data Protection Act, 2023 (Government of India).
- National Medical Commission, professional conduct regulations on consent and disclosure.










 Pinakamahusay na Ospital Malapit sa akin Chennai


