


إجابة مباشرة
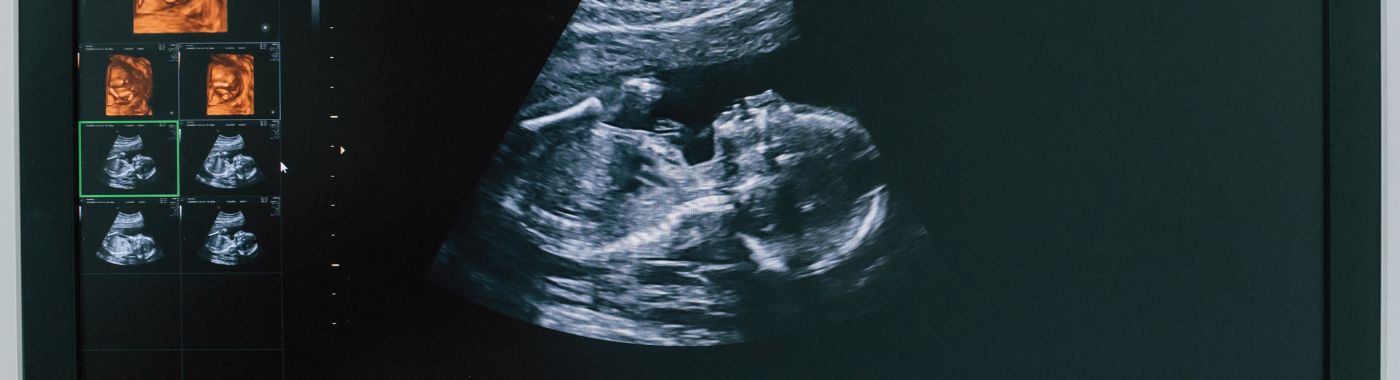
Fetal biometry is a set of ultrasound measurements, head, abdomen and thigh bone, used to estimate gestational age, track fetal growth and estimate fetal weight. Fetal biometry is part of a routine pregnancy scan (USG). The measurements are estimates, not exact figures, and always need interpretation alongside your dates and clinical history.
الوجبات الرئيسية
- Fetal biometry estimates size, not health: a measurement is one data point, not a diagnosis.
- Estimated fetal weight carries real error margins, which widen in the third trimester and with maternal body habitus.
- Dating is most reliable early: crown-rump length in the first trimester dates a pregnancy far better than late biometry.
- Biometry does not assess placental blood flow, movements or fetal wellbeing: Doppler, amniotic fluid assessment and monitoring answer those questions.
- Sex determination is illegal in India under the PC-PNDT Act, 1994; no scan report will disclose it.
في لمحة
| الميزات | التفاصيل |
|---|---|
| ما هو عليه | Ultrasound measurement of fetal body parts |
| القياسات الرئيسية | CRL, BPD, HC, AC, FL (occasionally HL, TCD) |
| طريق | Transabdominal; transvaginal sometimes in early pregnancy |
| الإشعاع | None, sound waves only |
| المدة النموذجية | Roughly 15-30 minutes; longer if views are difficult or a detailed anomaly scan is combined |
| التحضير | Usually none specific in later pregnancy; unit instructions apply |
| Who interprets | Radiologist / trained obstetric sonologist, with your obstetrician |
| النتائج تختلف | Results vary depending on individual clinical circumstances |
المعروف أيضا باسم
- Growth scan; fetal growth scan
- USG obstetrics; sonography in pregnancy; pregnancy scan
- Fetal measurements; biometry report
- Level 2 scan / anomaly scan (a different, broader study that يشمل biometry)
What fetal biometry is
Fetal biometry is the measurement part of an obstetric ultrasound. A sonologist freezes standard views and measures specific planes:
- Crown-rump length (CRL): head to bottom, used in the first trimester. CRL is the most reliable way to date a pregnancy.
- Biparietal diameter (BPD): side-to-side width of the skull in a standard transthalamic plane.
- Head circumference (HC): outline of the skull. HC is less affected by head shape than BPD.
- Abdominal circumference (AC): measured at the level of the stomach and umbilical vein. AC is the measurement most sensitive to growth problems and contributes most to weight estimation.
- Femur length (FL): the thigh bone shaft.
These values are entered into a formula (commonly Hadlock-type equations) to give an estimated fetal weight (EFW), and plotted on a growth chart as a centile.
Who should get this scan
- Anyone in routine antenatal care, biometry is part of standard dating, anomaly and third-trimester scans.
- Uncertain last menstrual period, irregular cycles, or conception after breastfeeding or contraception.
- Fundal height smaller or larger than expected on clinical examination.
- Hypertension in pregnancy, pre-eclampsia, or previous small baby or stillbirth.
- Gestational diabetes or pre-existing diabetes.
- Twins or higher-order pregnancy, where growth discordance matters.
- Reduced fetal movements, bleeding, or other concerns raised by your obstetrician.
- Maternal anaemia, thyroid disease, cardiac or renal disease, or a pregnancy on anticoagulation or other therapy requiring surveillance.
Frequency is individualised. Some pregnancies need one or two scans; others need serial scans every two to four weeks. Scans closer together than about two weeks can make growth trends harder, not easier, to read.
Why fetal biometry is done
- التعارف: to establish or confirm the expected date of delivery.
- Growth surveillance: to see whether size is tracking along a centile or drifting off it.
- Detecting suspected growth restriction: particularly through AC and EFW trends.
- Detecting suspected large-for-dates growth, relevant in diabetes.
- Twin monitoring: to look for growth discordance.
- تخطيط التسليم: as one input among many, alongside Doppler, fluid volume, maternal condition and gestation.
What fetal biometry cannot detect or exclude
This is the part most reports do not spell out.
- Fetal biometry does not measure fetal wellbeing. A baby on the 50th centile can still be unwell; a baby on the 5th centile can be constitutionally small and healthy.
- Biometry does not assess blood flow. Umbilical artery, middle cerebral artery and uterine artery Doppler are separate assessments.
- Biometry does not diagnose placental insufficiency. It can raise the suspicion; Doppler and surveillance refine it.
- Biometry does not screen for chromosomal conditions. Nuchal translucency with biochemistry, NIPT or diagnostic testing do that.
- Biometry is not an anomaly scan. Normal measurements do not exclude structural malformations, cardiac defects or brain anomalies.
- Biometry cannot give an exact birth weight. Estimated fetal weight has a recognised margin of error, typically wider at term and with a large baby, low fluid, or a difficult maternal window.
- Late biometry cannot reliably redate a pregnancy. Once dating is established early, later measurements assess growth, not dates.
- Biometry does not predict labour onset or the date of delivery.
- Biometry does not determine fetal sex in any report in India, and cannot legally be used for that purpose.
A normal scan describes what was seen on that day. It does not exclude problems developing later. If you notice reduced movements, bleeding, leaking fluid or severe headache after a normal scan, contact your obstetrician regardless of the report.
فحوصات ذات صلة ولكنها مختلفة
| فحص | السؤال يجيب عليه | How it differs from biometry |
|---|---|---|
| Dating scan (first trimester) | How many weeks pregnant am I? Is there a heartbeat? | Uses CRL; establishes dates that later scans are measured against |
| NT scan (11-13+6 weeks) | What is the chance of chromosomal conditions? | Screening measurement plus markers, not growth assessment |
| Anomaly scan (Level 2, around 18-22 weeks) | Is the structural anatomy as expected? | Detailed organ survey; includes biometry but is far broader |
| Growth scan (third trimester) | Is the baby growing along its trajectory? | Biometry-led, usually with fluid and Doppler |
| Umbilical/MCA Doppler | Is placental blood flow adequate? | Flow, not size; can be abnormal with normal biometry |
| Amniotic fluid assessment (AFI/SDP) | Is fluid volume normal? | Separate measurement, different clinical meaning |
| Biophysical profile / CTG (NST) | How is the baby coping right now? | Real-time wellbeing, not growth |
| تخطيط صدى القلب للجنين | Is the heart structurally and functionally normal? | Specialised cardiac study by a trained fetal cardiologist |
| مسح طول عنق الرحم | Is there preterm birth risk? | Usually transvaginal; unrelated to fetal size |
No single one of these is "better". They answer different questions, and which comes first depends entirely on the clinical problem, uncertain dates leads to a dating scan; reduced movements leads to CTG and fluid assessment; suspected growth restriction leads to biometry with Doppler.
كيفية تحضير
Preparation is an operational matter and differs between units and scanners. Your unit's written instructions take precedence over any general advice here.
- Early pregnancy scans: some units request a moderately full bladder for a transabdominal view; others prefer an empty bladder for a transvaginal scan. Ask when booking.
- Second and third trimester growth scans: usually no bladder preparation. A comfortable, partly empty bladder is often easier.
- لا حاجة للصيام for fetal biometry. Eat normally.
- ملابس: two-piece clothing with easy abdominal access.
- الوثائق: bring previous scan reports and your antenatal card. Growth trend interpretation depends on earlier measurements.
- التوقيت allow longer than the scan itself for registration and PC-PNDT Form F documentation.
إذا كنت مصابًا بمرض السكري وتتلقى علاجًا لخفض مستوى السكر في الدم
Do not skip meals or delay insulin or tablets while waiting for a scan. Fetal biometry does not require fasting. If any unit asks you to fast for a combined test, tell the staff about your medication and speak to your prescriber before changing timing.
If you have been told to restrict fluids
If you have heart failure, advanced kidney disease or a specified fluid restriction, do not load up on water for a "full bladder" instruction. Tell the sonography staff; they can usually scan without it or use an alternative approach.
If you have severe nausea or cannot lie flat
Tell the sonologist. Most scans can be done tilted slightly to the left side, which is also more comfortable in late pregnancy.
If you have had previous abdominal surgery or a raised BMI
Scar tissue and increased abdominal wall thickness can reduce image quality and widen measurement error. The scan may take longer or need repeating.
ماذا يحدث أثناء الفحص؟
You lie on a couch, warm gel is applied, and the sonologist moves a transducer over your abdomen. The sonologist confirms the heartbeat and presentation, captures standard measurement planes, and often checks fluid volume and placental position. In early pregnancy, a transvaginal scan may be offered for clearer views; a thin covered probe is inserted a short distance into the vagina. This is usually well tolerated but should be discussed and consented to first.
كم من الوقت يستغرق: a focused growth scan usually takes about 15-30 minutes of scanning time. A detailed anomaly scan or a twin scan takes considerably longer. Add waiting and paperwork time. Reporting time depends on the unit; many obstetric units hand over the report the same visit.
فهم تقريرك
A biometry report typically lists each measurement in millimetres, a gestational age equivalent for each, an average gestational age, an estimated fetal weight in grams, and a centile. Common phrases:
- "Corresponds to X weeks Y days": the size matches that gestation. Late in pregnancy this reflects size, not a change in your dates.
- "EFW ____ g, ____ centile": the estimated weight and where it sits on the chart used by that unit. Different charts (population-based versus customised) can give different centiles for the same baby.
- "AC lagging" or "asymmetric growth": the abdomen is smaller relative to head and femur, a pattern that raises the question of placental growth restriction and usually prompts Doppler.
- "Symmetrically small": all measurements small together; may be constitutional, or reflect early-onset causes.
- "Appropriate for gestational age (AGA)": size within expected range for dates.
- "SGA" / "LGA": small or large for gestational age, descriptive labels, not diagnoses.
A single centile means much less than a trend. Two or three scans showing steady tracking are more reassuring than one scan on a favourable centile. Only the doctor who requested the scan, seeing your full history, can interpret the report for your pregnancy.
Why we do not publish measurement tables
Normal ranges for CRL, BPD, HC, AC, FL and EFW vary by the reference chart in use, by gestational week and by population. Comparing your report to a number found online is a common source of unnecessary distress and of false reassurance. Use the centiles printed by the machine and chart your unit has selected, and discuss them with your obstetrician.
قد تكون النتائج مضللة في بعض الأحيان
Measurements that can read falsely small
- Head deep in the pelvis or against the uterine wall: HC and BPD may be underestimated.
- Oligohydramnios (low fluid): poorer outlines make AC harder to trace accurately.
- Breech or awkward position: femur or abdomen planes may be off-axis.
- تواريخ خاطئة: if the pregnancy is actually less advanced than recorded, a healthy baby looks small.
- Constitutionally small baby: small parents, especially in South Asian populations where average birth weights differ from Western reference charts. A population chart may label a normal baby SGA.
Measurements that can read falsely large
- Dolichocephaly or brachycephaly: head shape distorts BPD; HC is more robust.
- Over-generous AC tracing, including subcutaneous tissue or during fetal breathing movements.
- تواريخ خاطئة in the other direction.
- كثرة السوائل: can make outlines look generous.
Errors affecting estimated fetal weight in either direction
- EFW is a formula output. Small errors in AC magnify into large weight errors.
- Error margins are wider in the third trimester, at extremes of size, and with poor windows.
- Different formulae and different charts give different answers for the same baby.
- Operator experience and equipment quality both matter. Measurements are reproducible but not identical between observers.
For all these reasons, an EFW should never be treated as a birth weight prediction or as the sole basis for a decision about mode of delivery.
المخاطر والسلامة
Transabdominal obstetric ultrasound
Diagnostic ultrasound uses sound waves, not ionising radiation, and has a long record of use in pregnancy without established harm to the fetus at diagnostic output levels. Professional bodies nevertheless advise the ALARA principle, scanning for a clinical reason, with the lowest output and shortest time needed. Non-medical "keepsake" scanning is discouraged.
الموجات فوق الصوتية عبر المهبل
Transvaginal scanning is generally well tolerated and does not increase miscarriage risk. Mild discomfort or light spotting can occur. It may be avoided or modified with active bleeding, ruptured membranes or specific placental conditions, the sonologist will decide.
دراسات دوبلر
Doppler modes deliver higher acoustic output than routine imaging, so they are used for clinical indications and for limited durations rather than routinely in all pregnancies.
Indirect risks of over-interpretation
The commonest harm from biometry is not physical. An unexplained centile can lead to anxiety, repeat scans and, occasionally, unnecessary intervention. Balanced counselling matters as much as the measurement.
الأعلام الحمراء
Go to an emergency or labour room now
- Heavy vaginal bleeding, with or without pain
- Continuous severe abdominal pain or a hard, tender abdomen
- No fetal movements felt at all
- Fits, loss of consciousness, or severe breathlessness at rest
- Severe headache with blurred vision or upper abdominal pain (possible pre-eclampsia)
- Sudden gush of fluid before 37 weeks, or fluid that is green, brown or foul-smelling
Contact your obstetrician the same day
- Noticeably reduced or altered fetal movements
- A scan report stating absent or reversed umbilical artery end-diastolic flow, or severe oligohydramnios
- New or worsening swelling of face and hands with a rising blood pressure reading
- Fever above 38癈, burning urine, or persistent vomiting
- Any leak of fluid at term without contractions
Book a routine appointment
- A report saying the baby is on a lower or higher centile than before, with no symptoms
- Uncertainty about your dates or expected delivery date
- Wanting the report explained, or a second opinion on serial growth
- Questions about mode of delivery based on estimated weight
حالات خاصة
الحمل بتوأم أو أكثر
Each fetus is measured separately, and the difference between estimated weights (discordance) is tracked. Monochorionic twins need closer surveillance for twin-to-twin transfusion and selective growth restriction, on a schedule set by a fetal medicine team.
داء السكري أثناء الحمل
Biometry, particularly AC, is watched for accelerated abdominal growth. Estimated weight in diabetes has a wide error margin and should be combined with glycaemic control and clinical assessment, not used alone to decide on caesarean section.
ارتفاع ضغط الدم وتسمم الحمل
Growth restriction is common, and biometry is always paired with umbilical artery Doppler and fluid assessment. Doppler abnormality may appear before growth flattens.
Anaemia and haemoglobinopathies
Iron-deficiency anaemia and thalassaemia trait are common in India. Significant maternal anaemia is associated with lower birth weight, and fetal anaemia in some inherited conditions may show as hydrops rather than as altered biometry. Screening and haematology input matter alongside the scan.
Older mothers and those with kidney or heart disease
Surveillance is usually more frequent. Maternal condition, not the scan alone, often drives timing of delivery.
ساعد على الحمل
With IVF, gestational age is known precisely from the transfer date. Scan-based redating is not appropriate; the embryology dates stand.
Fetal biometry in the Indian context
- قانون منع الكشف المبكر عن الأمراض قبل الولادة وتحديد جنس الجنين، 1994: every obstetric ultrasound must be performed in a registered facility by a qualified, registered person, with Form F completed. Disclosure or determination of fetal sex is a criminal offence. You will be asked to sign a declaration that you have not requested sex determination. Registered centres display this notice openly; a centre that offers to tell you the sex is acting illegally.
- Charts and centiles: many Indian units use international reference charts, while average Indian birth weights differ from those reference populations. This can label constitutionally small but healthy babies as SGA. Some units use customised or population-specific charts. Ask which chart was used before acting on a centile.
- Low birth weight burden: low birth weight remains common in India and is influenced by maternal nutrition, anaemia, short interpregnancy interval and infection. Biometry detects the pattern; it does not treat the cause.
- المصطلحات التي ستسمعها: "USG obstetrics", "sonography", "growth scan", "Level 2 scan", "NT-NB scan", "anomaly scan", "Doppler study".
- وصول: availability of fetal medicine specialists and high-resolution equipment varies widely between metros, district hospitals and rural centres. A borderline finding is often best reviewed at a unit with fetal medicine support.
- خصوصية البيانات: scan images and reports are personal health data; handling by hospitals and any online booking tool falls under the Digital Personal Data Protection Act, 2023.
التكاليف والتأمين في الهند
Costs differ substantially and any figure here would mislead, so ask the unit for a written estimate before booking. Costs in India are typically quoted in ? per scan and are influenced by:
- Type of scan: a focused growth scan costs less than a detailed anomaly scan, fetal echocardiography or a multi-vessel Doppler study.
- Who performs and reports it: radiologist, obstetric sonologist or fetal medicine consultant.
- معدات: high-resolution 4D systems and specialised software cost more to run.
- الإعداد: government and municipal facilities, standalone diagnostic centres, and corporate hospitals differ widely. Many government facilities provide antenatal scans free or at nominal charge.
- City tier and whether the scan is out-of-hours or emergency.
- التجميع: some antenatal packages include a fixed number of scans.
التأمين: outpatient antenatal scans are frequently not reimbursed unless your policy has a maternity benefit or OPD cover, and maternity benefits usually carry a waiting period. If admitted, scans done during the admission are commonly part of the hospitalisation claim. Government schemes such as Ayushman Bharat PM-JAY and state maternity schemes cover defined services at empanelled facilities, confirm coverage with the facility's insurance desk in advance.
الخرافات والحقائق
| أسطورة | حقيقة |
|---|---|
| Too many scans harm the baby | Diagnostic ultrasound has no established fetal harm at diagnostic levels. Scans are still done for clinical reasons and for the shortest time needed, not for reassurance viewing. |
| The scan tells the exact birth weight | Estimated fetal weight is a formula-based estimate with a real margin of error, wider near term. |
| A low centile means something is wrong | Some healthy babies are simply small. A low centile prompts further assessment, not a diagnosis. |
| A normal growth scan means everything is fine | Biometry does not assess blood flow, anatomy in detail, or current wellbeing. Report new symptoms even after a normal scan. |
| A late scan can correct my due date | Dates are set by the earliest reliable scan or IVF date. Late measurements reflect growth, not gestation. |
| A big baby always means caesarean section | Mode of delivery depends on many factors. Estimated weight alone is an unreliable basis for that decision. |
| The sonologist can tell me the sex if I ask privately | Sex determination is a criminal offence in India under the PC-PNDT Act, 1994 for both the person asking and the person disclosing. |
الأسئلة المتكررة
How accurate is estimated fetal weight?
Estimated fetal weight is a calculation from measurements, not a weighing. It has a recognised percentage error that widens in the third trimester, with very large or very small babies, low amniotic fluid and difficult imaging windows. Serial trends are more informative than any single estimate, and clinical context always matters.
My baby is measuring two weeks behind. Should I worry?
Not necessarily. Possible explanations include inaccurate dates, a constitutionally small baby, measurement error, fetal position, or genuine growth restriction. Your obstetrician will usually check the chart used, compare earlier scans, and add umbilical artery Doppler and amniotic fluid assessment before drawing conclusions.
How often should growth scans be repeated?
Frequency is individual. Uncomplicated pregnancies typically need few scans, while hypertension, diabetes, twins or previous growth restriction usually warrant more. Repeating biometry sooner than about two weeks apart makes growth trends unreliable, because measurement error can exceed genuine growth over short intervals.
Is a growth scan the same as an anomaly scan?
No. An anomaly scan, often around 18 to 22 weeks, is a detailed structural survey of the brain, heart, spine, abdomen and limbs, and includes biometry. A third-trimester growth scan focuses on size, fluid and often Doppler, and is not a repeat anatomy assessment.
Do I need a full bladder or to fast?
Fasting is not required for fetal biometry. Bladder instructions differ: some early-pregnancy transabdominal scans are easier with a moderately full bladder, while later scans usually need no preparation. Follow the written instruction from your scan unit, and tell staff if you have a medical fluid restriction.
Can the scan predict when I will deliver?
No. Fetal biometry contributes to the estimated due date when performed early, but it cannot predict the day labour will start. Timing of delivery decisions rests on gestational age, growth and Doppler trends, amniotic fluid, maternal health and obstetric history together.
Why does my report not mention the baby's sex?
Indian law prohibits determining or disclosing fetal sex during any prenatal test under the PC-PNDT Act, 1994. Registered ultrasound facilities must maintain Form F records and display this prohibition. This restriction exists to address sex-selective termination and applies to every obstetric scan in the country.
What does "asymmetric growth restriction" mean in my report?
Asymmetric growth means the abdominal circumference is proportionally smaller than the head and femur. That pattern often points towards reduced placental supply, where the fetus preserves brain growth. It usually prompts Doppler studies, fluid assessment and closer surveillance rather than immediate delivery.
Who interprets my fetal biometry report?
The scan is performed and reported by a radiologist or trained obstetric sonologist, but the clinical meaning comes from the obstetrician who requested it, using your dates, examination, blood pressure, glucose status and previous scans. Never act on a centile or measurement read off the internet.
مصادر
- Pre-conception and Pre-natal Diagnostic Techniques (Prohibition of Sex Selection) Act, 1994 and Rules, Ministry of Health and Family Welfare, Government of India
- International Society of Ultrasound in Obstetrics and Gynecology (ISUOG), Practice Guidelines on performance of first-trimester and mid-trimester fetal ultrasound
- Royal College of Obstetricians and Gynaecologists, Green-top Guideline on the investigation and management of the small-for-gestational-age fetus
- World Health Organization, Recommendations on antenatal care for a positive pregnancy experience
- American Institute of Ultrasound in Medicine, Statements on prudent use and safety of obstetric ultrasound
- Federation of Obstetric and Gynaecological Societies of India (FOGSI), guidance on obstetric ultrasound practice and PC-PNDT compliance
- قانون حماية البيانات الشخصية الرقمية لعام 2023، حكومة الهند










 أفضل مستشفى بالقرب مني في تشيناي


