


Direct answer
ELISA (Enzyme-Linked Immunosorbent Assay) is a laboratory method that uses antibody-antigen binding and an enzyme-linked colour signal to detect or measure a specific substance, an antibody, antigen, hormone or protein, usually in blood. ELISA is mostly a screening and quantification tool; several ELISA results need a confirmatory test before any diagnosis is made.
Key takeaways
- ELISA is a method, not a single test. An HIV ELISA, a dengue NS1 ELISA and a thyroid hormone ELISA answer entirely different questions.
- A reactive ELISA is not a diagnosis. Screening assays are designed to miss few true cases, which means some reactive results are false positives.
- A non-reactive ELISA does not exclude infection. Antibodies take time to appear; testing during the window period can give a negative result in a genuinely infected person.
- Reference ranges belong to the reporting laboratory. Values from different kits and platforms are often not interchangeable.
- Preparation depends on the analyte, not on the ELISA technique itself. Your lab's or doctor's instructions take precedence.
At a glance
| Item | Detail |
|---|---|
| What it is | Plate-based immunoassay detecting a specific antibody, antigen, hormone or protein |
| Sample | Most often venous blood (serum or plasma); some assays use urine, saliva, stool or CSF |
| Blood draw time | Usually a few minutes |
| Result type | Reactive / non-reactive, an index or ratio, or a numerical concentration |
| Main role | Screening, antibody detection, quantifying hormones and proteins, monitoring |
| Key limitation | Cross-reactivity, window period, kit-to-kit variation; often needs confirmation |
| Fasting | Not needed for most ELISA tests; required only for certain analytes |
Also known as
- Enzyme-Linked Immunosorbent Assay
- EIA (enzyme immunoassay)
- Elisa test, "Eliza test" (common spelling in Indian lab requisitions and patient queries)
- Antibody test / antigen test, when named by what it measures (for example "HIV ELISA", "dengue IgM ELISA")
- Screening test / confirmatory-pending test, in the context of infection screening
What ELISA is
ELISA is a laboratory technique performed on a microtitre plate with many small wells. The well surface is coated with an antigen or an antibody that will bind only to the target substance. The patient sample is added, binding occurs, unbound material is washed away, and an enzyme-linked detection antibody is added. The enzyme then reacts with a substrate to produce colour. A photometer measures the colour intensity as optical density (OD), which relates to the amount of target present.
ELISA formats differ in how the target is captured and detected:
- Direct ELISA: a single labelled antibody binds the antigen. Simple, fewer steps, generally lower amplification.
- Indirect ELISA: a primary antibody binds the target and a labelled secondary antibody binds the primary. Widely used for antibody detection, such as many infection serology tests.
- Sandwich ELISA: the antigen is captured between two antibodies. Often used for measuring proteins and hormones in complex samples.
- Competitive ELISA: the target in the sample competes with a labelled version for binding. Useful for small molecules with only one binding site.
The format used is chosen by the laboratory. The patient experience is the same regardless of format.
Why ELISA is done
- Infection screening and serology: HIV, hepatitis B and C, dengue (NS1 antigen, IgM, IgG), chikungunya, scrub typhus, leptospirosis, typhoid, hepatitis A and E, syphilis, toxoplasmosis and rubella, among others.
- Autoimmune assessment: antibodies such as anti-tissue transglutaminase in suspected coeliac disease, anti-CCP in suspected rheumatoid arthritis, and various ENA antibodies.
- Hormones and proteins: some laboratories quantify hormones, tumour markers or specific proteins by ELISA, although many large labs now use chemiluminescence platforms instead.
- Allergy testing: allergen-specific IgE assays.
- Monitoring: tracking a measured protein or antibody level over time on the same platform.
- Blood bank and public health screening: donor screening and surveillance programmes.
Who should get an ELISA test
- People with symptoms suggesting a specific infection the assay can detect, for example fever with body ache and low platelets in a dengue-endemic season.
- People with a known exposure or risk situation, such as a needlestick injury, unprotected sexual exposure, or a blood transfusion in an unscreened setting.
- Anyone advised HIV or hepatitis screening before surgery, dialysis, pregnancy care, or as part of a blood donation programme.
- People with suspected autoimmune disease, where an antibody panel supports the clinical picture.
- People with suspected allergy, where specific IgE testing adds to a careful history.
- People on treatment whose response is tracked by a measured antibody or protein level.
ELISA is not a general health check-up test and is not useful without a clinical question behind it. Testing without a reason increases the chance of a misleading result.
What ELISA cannot detect or exclude
- ELISA cannot detect what it was not designed for. An HIV ELISA says nothing about hepatitis; each assay targets one analyte.
- A non-reactive antibody ELISA does not exclude recent infection. During the window period before antibodies develop, results can be negative despite genuine infection. The window varies by infection and assay generation.
- A reactive ELISA does not confirm disease. Screening assays favour sensitivity. Reactive results require confirmatory or supplemental testing appropriate to the infection.
- ELISA usually cannot distinguish past from current infection when only IgG is measured. Antibodies can persist for years after recovery or vaccination.
- ELISA does not measure the organism itself in most formats. Nucleic acid tests such as PCR detect genetic material and can be positive earlier in many infections.
- ELISA does not assess severity, organ damage or prognosis. An antibody titre is not a measure of how ill a person is.
- ELISA does not identify which strain, serotype or resistance pattern is present, except where the assay is specifically designed for that purpose.
If symptoms persist despite a normal or non-reactive ELISA result, go back to your doctor. A negative result describes what the assay detected, not what does or does not exist in the body.
Related but different tests
| Test | What it detects | How it differs from ELISA |
|---|---|---|
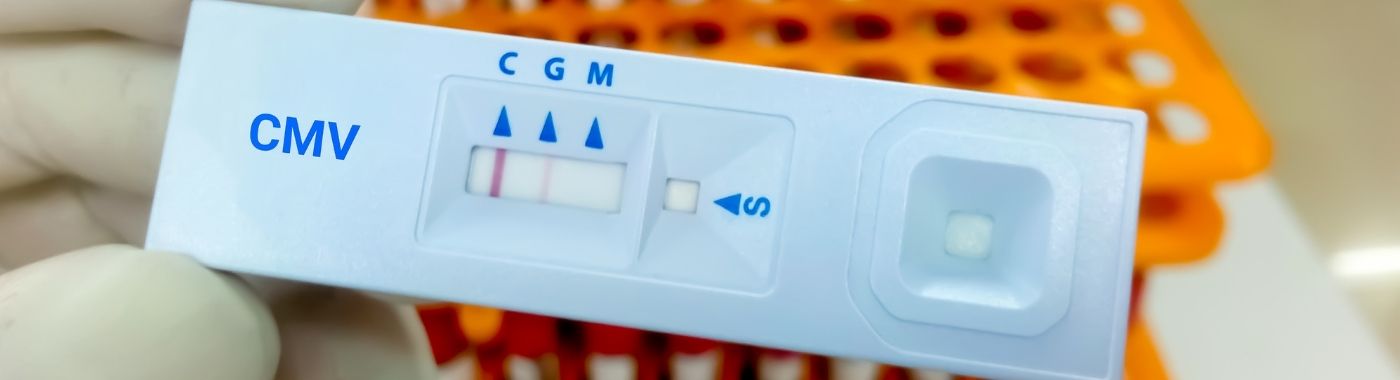
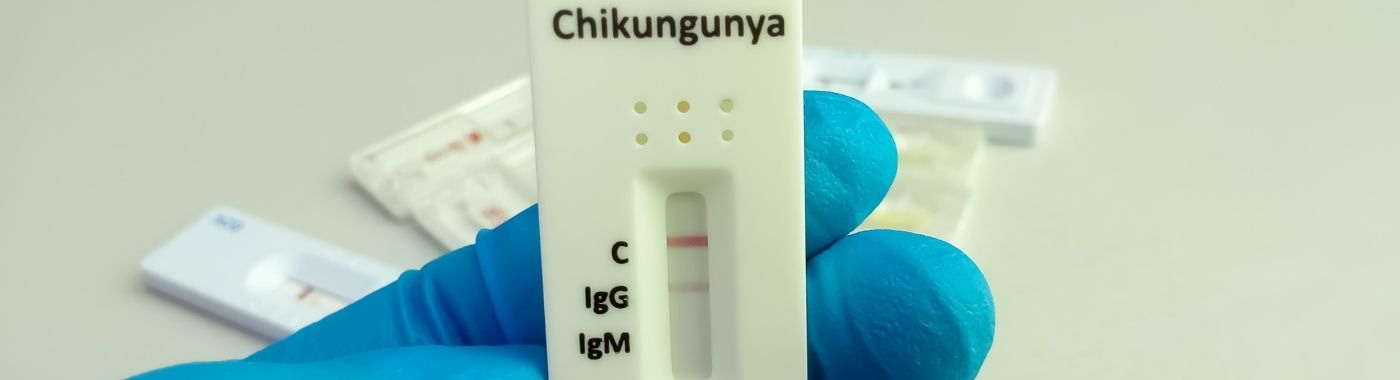
| Rapid card test / lateral flow | Antibody or antigen, visually read | Faster and needs no plate reader, but generally less sensitive and gives a yes/no answer rather than a value. Often used for screening where lab access is limited. |
| CLIA / ECLIA (chemiluminescence) | Same analytes as many ELISAs | Uses a light signal instead of colour. Usually automated, often more sensitive and faster in high-volume labs. Values are not always interchangeable with ELISA values. |
| Western blot / immunoblot | Antibodies against individual proteins | Used as a supplemental or confirmatory test after a reactive screening assay, not as a first-line screen. |
| PCR / NAAT | Genetic material of the organism | Detects the pathogen itself, often positive earlier than antibody tests. Answers "is the organism present now", while antibody ELISA answers "has the immune system responded". |
| Culture | Live organism grown in the lab | Can identify the organism and test antibiotic susceptibility. Slower, and negative if the organism is fastidious or antibiotics were already started. |
| Skin prick test (allergy) | Immediate skin reaction to an allergen | Performed on the patient, not on a sample. Specific IgE ELISA is an alternative when skin testing is not suitable. |
No single method is superior across the board. The right test depends on the illness, how many days symptoms have been present, and what decision the result will guide.
How to prepare
Preparation depends on what is being measured, not on ELISA as a technique. Your collection centre's instructions override any general guidance here.
- Fasting: most ELISA tests, including infection serology, need no fasting. Fasting applies only to certain analytes and only if your laboratory specifies it.
- Timing: some hormones vary through the day or the menstrual cycle. Ask whether your sample should be taken at a particular time.
- Medicines and supplements: tell the laboratory and your doctor everything you take, including AYUSH preparations, herbal products, gym supplements and biotin. Do not stop any prescribed medicine to prepare for a test unless the prescriber tells you to.
- Recent vaccination, blood transfusion or immunoglobulin therapy: mention these, as they can affect antibody results.
- Symptom timeline: tell the requesting doctor which day of illness you are on. For many infections, an antibody test drawn too early is uninformative.
- Identification and consent: HIV testing in India follows a counselling and informed-consent framework, with confidentiality protections.
Pregnancy
Several ELISA-based screens are part of routine antenatal care. Interpretation of infection serology in pregnancy differs from that in non-pregnant adults and should be done by the treating obstetrician.
Children
Blood volume is reduced for paediatric samples. In infants, maternal antibodies crossing the placenta can make an antibody ELISA reactive without the baby being infected; antigen or nucleic acid testing may be preferred.
Older adults and people with chronic illness
Immune responses can be weaker with age, immunosuppressive therapy, advanced kidney or liver disease, or cancer treatment. Antibody-based ELISA can be falsely non-reactive in these situations.
People with diabetes on glucose-lowering therapy
If a fasting sample is requested alongside the ELISA, discuss timing and your medication schedule with the prescriber beforehand to avoid hypoglycaemia. Do not skip or delay doses without advice.
What happens during the test
- Sample collection: for a blood-based ELISA, a phlebotomist cleans the skin, applies a tourniquet and draws blood from an arm vein. The draw itself usually takes a few minutes; total time at the collection centre depends on the queue.
- Other samples: urine, saliva, stool or CSF collection follows the method appropriate to that sample. CSF is collected by a doctor during a lumbar puncture.
- In the laboratory: serum or plasma is separated, added to coated wells, incubated, washed, and read on a plate reader. Many ELISA plates are run in batches, so a sample may wait until enough samples accumulate.
- Validation: controls and calibrators are run alongside patient samples. If the controls fail, the batch is repeated.
How long the process takes
- Your time at the centre: typically short, registration, collection, and you leave.
- Laboratory processing: the assay itself commonly runs over a few hours, including incubation and washing steps.
- Reporting: depends on whether your laboratory runs the assay daily or in scheduled batches, and whether the sample is sent to a reference laboratory. Batched and outsourced tests take longer. Ask your collection centre for its reporting schedule for your specific test.
- Reactive screening results may take longer overall, because confirmatory or supplemental testing is added before a final report is released.
Understanding your ELISA report
ELISA reports appear in one of three broad forms.
- Qualitative: "Reactive" or "Non-reactive" (sometimes "Positive"/"Negative"). Used for most infection screening.
- Semi-quantitative: an index, ratio or S/CO (signal-to-cut-off) value compared against the kit's cut-off. A value close to the cut-off is in the grey zone and is less reliable.
- Quantitative: a concentration in units such as IU/mL, ng/mL or U/mL, read from a standard curve.
Points that patients frequently misread:
- The reference range printed on your report belongs to that laboratory and that kit. Do not compare a number from one lab with a number from another lab or a different platform.
- A higher number does not mean a more severe illness. Antibody levels reflect immune response, not disease severity.
- Grey-zone or borderline results are common and are not "half positive". They usually mean the test should be repeated after an interval or a different method should be used.
- IgM broadly suggests a recent response and IgG a past or established response, but overlap is substantial and neither can be read in isolation.
Every ELISA result must be interpreted in clinical context by the doctor who requested it, alongside your symptoms, exposure history and other tests. Results vary depending on individual clinical circumstances.
When ELISA results can be misleading
Falsely positive or falsely raised
- Cross-reactivity: antibodies against a related organism can bind the assay antigen. This is well described among flaviviruses, for example dengue and other related infections.
- Autoantibodies and rheumatoid factor: can interfere with antibody-based assays.
- Heterophile antibodies and human anti-mouse antibodies: can bridge the capture and detection antibodies and create a false signal, especially in sandwich formats.
- Pregnancy, recent vaccination, multiple transfusions and some chronic diseases: recognised causes of non-specific reactivity in some screening assays.
- Biotin supplements: can interfere with certain streptavidin-biotin based immunoassays. Mention high-dose biotin before testing.
- Technical issues: incomplete washing, contamination between wells, or sample carry-over.
Falsely negative or falsely lowered
- Window period: testing before the antibody response has developed.
- Immunosuppression: HIV, chemotherapy, steroids, biologic therapy, advanced CKD or liver disease can blunt antibody production.
- Prozone (hook) effect: extremely high analyte concentration can paradoxically reduce the signal in some formats.
- Sample handling: haemolysis, lipaemia, delayed separation, incorrect storage or an inappropriate collection tube.
- Very early antigen clearance: for antigen assays such as dengue NS1, sensitivity falls as the illness progresses.
If the result does not fit the clinical picture, the correct next step is to discuss repeat or alternative testing with your doctor, not to accept the number at face value.
Risks and safety
Venous blood sample
Common and usually minor: brief pain, bruising, and lightheadedness. Less common: a small haematoma, or feeling faint during the draw. Infection at the puncture site is uncommon when standard aseptic technique is used. Tell the phlebotomist if you take blood thinners, bleed easily, or have fainted during a blood test before.
Urine, saliva and stool samples
These collections do not involve needles and carry no physical risk. Accuracy depends heavily on collecting the sample exactly as instructed.
Cerebrospinal fluid samples
When an ELISA is performed on CSF, the risk lies with the lumbar puncture itself, not the assay. Headache after the procedure is the most frequent complaint; bleeding and infection are uncommon. The procedure is performed only when clinically justified.
Risks of the result rather than the procedure
A false positive can cause anxiety and unnecessary further testing. A false negative can delay diagnosis. This is why reactive screening results are confirmed and why clinical context matters more than the printed value.
Red flags
Emergency now
- High fever with breathlessness, chest pain, confusion, seizures, or reduced responsiveness.
- Bleeding from gums, nose, vomit or stools, black tarry stools, or bleeding into the skin, particularly during a dengue-like illness.
- Severe abdominal pain, persistent vomiting, cold clammy skin, rapid weak pulse, or a sudden drop in urine output.
- Signs of a severe allergic reaction after any exposure: swelling of the lips or tongue, difficulty breathing, collapse.
Same day
- Fever continuing beyond a few days with worsening weakness, or fever returning after settling.
- Yellowing of the eyes or skin, dark urine, or new confusion in someone with liver disease.
- A reactive HIV, hepatitis B or hepatitis C screening result, arrange prompt review and confirmatory testing with counselling.
- Needlestick or significant exposure injury, this is time-critical, because preventive treatment for some infections is most useful when started early.
- Spreading redness, swelling or pus at a blood-draw site.
Routine appointment
- Borderline or grey-zone results needing a planned repeat.
- Non-reactive results with ongoing but stable symptoms.
- Reviewing an autoimmune or allergy antibody panel.
- Monitoring a quantitative level over time.
Special situations
Pregnancy
Antenatal screening in India commonly includes HIV, hepatitis B and syphilis testing, and may include other serology depending on the clinical situation. Some assays show more non-specific reactivity in pregnancy, so a reactive screen is confirmed before any conclusion is drawn. Treatment decisions are made jointly by the obstetrician and, where relevant, an infectious disease specialist.
Newborns and children
Maternal IgG antibodies persist in an infant for months. An antibody ELISA in a young infant may therefore reflect the mother's status rather than the baby's. Antigen detection or nucleic acid testing is preferred for early infant diagnosis of several infections.
People living with HIV or on immunosuppressive therapy
Antibody responses may be weak or absent. Antigen-based or molecular testing is often more reliable in this group.
Chronic kidney disease and dialysis
People on maintenance haemodialysis undergo periodic hepatitis B and C screening. Responses to hepatitis B vaccination may be lower, and post-vaccination antibody testing is sometimes advised by the treating nephrologist.
Heart failure and fluid restriction
The ELISA itself imposes no fluid requirement. If a collection centre asks you to drink a specific volume of water for an unrelated test on the same visit, tell staff about any fluid restriction before complying.
Older adults
Fever and infection can present atypically, with confusion or falls rather than high temperature. A non-reactive serology result in an older adult with unexplained illness should not close the investigation.
ELISA in the Indian context
- Vector-borne and tropical infections dominate demand. Dengue NS1, dengue IgM and IgG, chikungunya IgM, scrub typhus IgM, leptospirosis and enteric fever serology are ordered heavily during and after the monsoon in much of the country.
- Cross-reactivity matters more where several flaviviruses circulate. A reactive dengue IgG in someone with past exposure or in an endemic area needs careful reading against the clinical picture.
- Hepatitis A and hepatitis E are common causes of acute viral hepatitis in India, and IgM serology by ELISA is a standard part of the workup for acute jaundice.
- Anti-tubercular therapy and hepatotoxicity: when jaundice develops on ATT, viral hepatitis serology is often performed to distinguish drug injury from infection. Never stop TB medication on your own, speak to the treating doctor.
- Herbal, AYUSH and gym-supplement related liver injury is an increasingly recognised cause of abnormal liver tests in India. Disclose all such products when serology is requested.
- Serology for tuberculosis is not recommended. Blood antibody tests for active TB have been advised against by the World Health Organization and are banned for commercial use in India. If a laboratory offers an ELISA "TB blood test" for active TB, question it. Interferon-gamma release assays are a different category of test and are used for latent infection, not to diagnose active TB by themselves.
- HIV testing framework: India's national programme uses a defined testing strategy with counselling and confidentiality. A single reactive screening test is never reported as an HIV diagnosis.
- Data protection: personal health data collected through hospital forms, portals and home-collection apps is subject to the Digital Personal Data Protection Act, 2023.
Cost and insurance in India
ELISA test prices differ widely because "ELISA" covers many different assays. Costs are generally modest for common single-analyte serology and higher for specialised autoimmune or allergen panels. Prices in India are quoted in ? and vary between cities, between government and private facilities, and between standalone laboratories and hospital labs.
Factors that affect the price:
- Which analyte is tested, and whether it is a single test or a panel.
- Whether the assay is run in-house or outsourced to a reference laboratory.
- Accreditation status of the laboratory and the kit manufacturer used.
- Whether confirmatory or supplemental testing is included in the reported price.
- Home sample collection charges and urgent-processing charges.
- City, facility type, and any bundled health package.
Insurance: diagnostic tests done on an outpatient basis are often not reimbursed unless the policy includes OPD or diagnostic cover. Tests performed during an admitted hospital stay are usually covered as part of the claim, subject to policy terms. Several national programmes provide HIV, hepatitis and antenatal screening free of charge at government facilities. Confirm charges with the laboratory and coverage with your insurer before testing, as costs listed anywhere online are indicative only and change over time.
Myths and facts
| Myth | Fact |
|---|---|
| A reactive ELISA means you have the disease. | Screening assays are tuned to miss few true cases, which produces some false positives. Confirmatory testing is required before a diagnosis. |
| A negative ELISA rules out infection. | A negative result does not exclude infection, particularly during the window period or in immunosuppressed people. Persistent symptoms warrant review. |
| A higher antibody number means a worse infection. | Antibody level reflects immune response, not disease severity or prognosis. |
| ELISA can diagnose active tuberculosis from blood. | Antibody-based blood tests for active TB are not recommended and are prohibited for commercial use in India. |
| Results from two labs can be compared directly. | Different kits, platforms and units mean values are frequently not interchangeable. Monitor on the same laboratory where possible. |
| Fasting is needed for every ELISA test. | Most ELISA tests, including infection serology, do not require fasting. Requirements depend on the specific analyte. |
| Home kits are equivalent to a lab ELISA. | Home kits are usually rapid tests, not laboratory ELISAs. A reactive or unexpected home result should always be checked with formal laboratory testing. |
Frequently asked questions
What is an ELISA test used for?
ELISA is used to detect or measure a specific antibody, antigen, hormone or protein in a sample. Common uses in India include screening for HIV and hepatitis, diagnosing dengue and other tropical infections, testing autoimmune antibodies, and measuring allergen-specific IgE. The purpose depends entirely on which analyte is requested.
How accurate is an ELISA test?
Accuracy differs by assay, manufacturer and the stage of illness at which the sample was taken. Screening ELISAs are designed to detect most true cases, which means some reactive results are false. No single figure applies to all ELISA tests, and reactive screening results are confirmed with a different method.
Is fasting required before an ELISA test?
Usually not. Infection serology, autoimmune antibody panels and allergy IgE tests generally do not need fasting. Fasting applies only to specific analytes, and only if your laboratory states it. Confirm with the collection centre when booking, since protocols differ between units.
What does a borderline or grey-zone ELISA result mean?
A grey-zone value sits close to the kit's cut-off, where the assay is least reliable. It is neither a weak positive nor a diagnosis. The usual response is to repeat the test after an interval, test a fresh sample, or use a different method. Discuss the next step with your doctor.
How is ELISA different from a PCR test?
ELISA usually detects the immune response or a protein, while PCR detects the organism's genetic material. PCR often turns positive earlier in infection; antibody ELISA becomes useful later, once the immune response develops. The two answer different questions and are frequently used at different points in the same illness.
Can medicines or supplements affect ELISA results?
Yes. Immunosuppressants, steroids, recent immunoglobulin therapy and high-dose biotin can all influence results, and herbal or gym supplements may affect related tests. List everything you take when the sample is collected. Do not stop any prescribed medicine to prepare for a test without speaking to the prescriber.
Can ELISA detect disease at a very early stage?
Not always. Antibody-based ELISA depends on the immune system having responded, so very early infection can be missed. Antigen assays such as dengue NS1 can detect earlier but lose sensitivity as illness progresses. Telling your doctor which day of illness you are on helps in choosing the right test.
Are home ELISA kits reliable?
Most home kits are rapid lateral-flow tests rather than true laboratory ELISAs. They can be convenient for screening, but they are generally less sensitive, are read by eye, and give no numerical value. Any reactive, unexpected or symptom-discordant home result should be repeated in an accredited laboratory.
How soon after exposure should an ELISA be done?
The right timing depends on the infection and the assay type. Testing too early can give a false negative because antibodies have not yet appeared. After a significant exposure, seek medical advice promptly rather than testing immediately, some preventive treatments are time-sensitive and should not wait for a test result.
Sources
- World Health Organization, guidance on HIV testing services and on commercial serodiagnostic tests for tuberculosis.
- National AIDS Control Organisation (NACO), Ministry of Health and Family Welfare, Government of India, national HIV testing strategy and counselling guidelines.
- National Centre for Vector Borne Diseases Control (NCVBDC), Government of India, national guidelines for dengue diagnosis and case management.
- Indian Council of Medical Research, guidance on laboratory diagnosis of tropical febrile illnesses.
- Digital Personal Data Protection Act, 2023, Government of India.
- Clinical and Laboratory Standards Institute, guidance on immunoassay interference and quality control.










 Best Hospital Near me Chennai


